Showing posts with label fundo. Show all posts

Friday, December 7, 2012

Nissens are Fundo! G I have a Tubie!

So I had an excellent conversation with the doctor today and got all my questions answered. It really pays to do your research. All the pieces finally came together and we reviewed her symptomology and are in total agreement that she already has severe reflux with atypical presentation of almost exclusively respiratory symptoms. You just don't hear of babies with severe reflux that never throw up, but my baby girl loves to be unique! That is what has made it so puzzling and idiopathic this entire time, and hard for me to research too.
What? You thought I was coming home Wednesday?
I wasn't gonna let you off that easy!
I still haven't hit your insurance cap yet...
They think that her RAD is very reactive, but to the micro-aspirations and silent reflux and not necessarily other triggers. This has me more relaxed now that she won't be under house arrest after all, though we will of course be taking plenty of precautions.

So as you can deduce, we are going ahead with the Nissen Fundoplication surgery as well as the G-tube. The fundo will eliminate or at least significantly reduce the reflux she has now. The G-tube will reduce stomach size and exacerbate the reflux so it makes the fundo even more necessary. Not to mention her RAD breathing treatments also aggravate reflux! I am fully confident that we are making the right decision. That is especially important because with her atypical GERD presentation we won't really have much of anything to confirm that we did the right thing. Hopefully her RAD will be less problematic and we won't have aspiration pneumonia, but aside from that we won't see a reduction in severe vomiting and pain and all the other typical GERD symptoms that lead most parents to this surgery far later in the game.

I've discussed the surgery with Tara who is all for it, mostly because she hates tubes in her mouth and nose and tape on her face. She is full of the cute every time I see her and has every nurse wrapped around her finger. She is the biggest baby in the NICU and the oldest, so she interacts and sleeps less and the LOVE her! Little Miss Popular.
It is good to finally nail down what I have suspected since her 2nd Delhi hospitalization. And if it took this long to finally confirm it in the US, I'm not going to fault them in India for not confirming it sooner but only failure to follow up diagnostically and treat it properly once Dr. Saluja suggested it as a possibility. I don't even know if they can do an Impedence probe test in Delhi, though surely they do Nissen's and G-tubes. They certainly couldn't do viral testing.

It is also a relief to know that it wasn't anything I did wrong or could have prevented from happening this entire time. It is so hard as a Mom not to second guess yourself about what you could have done differently to prevent it when you see your child suffer from something. Whether she was on a plane and caught a rhinovirus or not, she was doomed to wind up in a hospital with pneumonia soon anyway.

Swaddling. It does a baby good.

Vivek in the "straightjacket" swaddler Mommy
reserves for fits of the most epic proportions.
As a side note, Dr. Treen also reassured me that the reason the nurses and doctors don't react so much to her O2 dips during crying is that the monitor is not reliable during a crying episode and it is not anywhere near where it is reported to be. So I don't have to drop everything with my son to comfort her until she calms down unless she starts wheezing very badly. Good to know!

We know that the Nissen can have some complications, and it is not a cure all. It can be too tight where they have swallowing difficulty and it will set us back in bottle feeding and create an oral aversion along with gas bloat pain and venting issues. It can be too loose and she could still burp and throw up and reflux. The three little Nissens. This one is too tight. This one is too loose. Hopefully ours will be just right, though they loosen over time. It is the mose common surgery they do in the NICU, and this is a big and busy and well reputed hospital with very experienced surgeons so I have high hopes that hers will go well. It does loosen as they grow, especially in the first year, so if that happens before she outgrows her feeding issues/reflux then it may need to be redone/tightened.


Daddy and your brother seriously need some more estrogen to balance out the power in this household! Come home soon!

For those of you reading this with similar issues, I found search terms of "silent reflux" and "microaspiration" to be the best place to start, but had trouble finding anything written by someone who had a Nissen done on an infant with these specific and exclusive respiratory symptoms. I'm sure it happens, but the people who write about their Nissen experience are your typical refluxers who have been knee deep in vomit for a year or two with issues like failure to thrive and oral aversions and they are making desperate posts online. I take all anecdotal evidence I find on forums with a grain of salt, because it is not truly evidence and scientific articles are of the most value. Keep in mind that there are many Nissen horror stories out there, but the people who have had problems are a population that:
     1. Typically have more medically complex children where other things can be affecting their outcomes
     2. Are the people who are most motivated to follow forums and write about it. The folks that had things go great often move on with their life and abandon the interweb oversharing. :)

Dr. Treen assured me that they routinely do an upper GI series/manometry to rule out motility issues before they do any Nissen so they will know if a pyloroplasty or intestinal repositioning is in order. That was done this afternoon, and while I don't know results yet I'm sure they are negative. We already agreed she doesn't have any symtoms of motility issues, but I feel better that we are ruling it out for certain to avoid extra surgeries.

I told the doctor that I am accepting she won't be home by Christmas, but she told me that depending on whether we could get lucky and have an availability in the next few days it might still be possible. It depends on a lot of things. Laparascopy has faster recovery times and is safer, but if the surgeon decides that it is too risky because filling her tummy up with gas will put too much pressure on her diaphragm we'll do it as an open surgery with a longer recovery and more cool scars for her to show off. Mommy and Daddy have both had abdominal laparoscopy so here's hoping we will all have matching scars! It also depends on her breathing after surgery, because it is quite possibly she could go back on the ventilator for a few days. But then again she might not need it at all. As usual, Tara is in charge and running the show here and I'll just have to see whether she decides to celebrate the holidays at home or not. We'll find a way to celebrate no matter what! As for Vivek he will be content just to stare at the Christmas lights.


I'm hoping for a button style to be put in right away, but it is very common that  PEG tube is put in first and once the stoma heals a 3 months or so later they replace it with a Mic-Key button or Mini One button. Picture of the PEG below:

As you can see, the PEG is temporary for a reason. It is a big bulky pain in the ass and difficult to hide under clothing and super easy for your grabby little baby to pull out with their tiny flailing fists. But whether we start with a PEG or not, I'm going to fight as hard as I can for the Mini-One button by AMT because due to the low profile and failure rates alone it seems far better than the standard Mic-Key button.
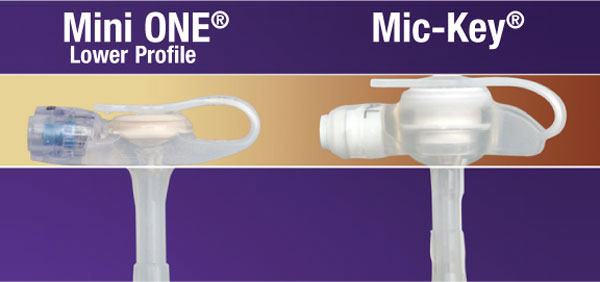
Mic-Key® BalloonMini ONE® Balloon
Time to First Balloon Failure62 hours500 hours
Time to Last Balloon Failure185 hours2038 hours
Average Balloon Lifespan98 hours1187 hours

It seems like the Mic-Key winds up needing replacement due to ballon or other failure every 3 months or so. Here is a video that showed me what replacing it is like, and it is less scary than I thought. The baby certainly doesn't seem to be in pain.


Once we find out availability we will meet and consult with the GI surgeon who will do both procedures at once. I'm hoping for a real asshole. I believe that all the best surgeons are assholes. Bad bedside manner but an excellent mechanic. Those docs with a good bedside manner can compensate for not being as good, but a real jerk is still in the business for a good reason. :)

We will still be bottle feeding and use her G tube to finish off. She has a new time limit of 15 minutes to help reduce the risk of aspirations during swallowing, but when she wants to she can suck down a full 45mL during that time frame out of her 75. I'm hoping we can slowly increase bottle feeds and keep her very oral, but I have no idea how long it will be until she can be fully bottle fed. I do know they typically keep a G-tube in for 6 months after last usage before removal. The stoma heals up pretty quickly by most reports.
Today I decided to spur on my newfound positive state of mind by purchasing some G-tube covers off of Etsy. Here are the ones I ordered: http://www.etsy.com/shop/MakeLemonaid  I like these ones with covers better for grabby little hands at http://www.feedingessentials.com/#!shop-online, but I'm going to see if a crafty friend can help me make some more. Here is a link to a great website with every G-tube cover you can buy.
http://www.feedingtubeawareness.org/Gtube-Pads.html  And there are also belts to hold tubing secure on this website, which are especially necessary if your child has a GJ and/or is continuously fed or fed at night and could get tangled up.
I’m trying to learn what the best fabrics I can buy are and how to avoid edges and lots of stitching especially near the center. Stomach liquid leaking can absorb and dry and then stick, and you want absorption but not sticking. Absorption is important because the stomach acid can leak out the edges and cause irritation, infection, and some raised red skin called granulomas. The G tube covers serve the same purpose as gauze or makeup sponges folks use for that purpose, but are way more fashionable! My princess needs her tube to look FABULOUS!


I plan on emptying the hat/shoe/sock drawer in the high boy and making that the G-tube supply drawer. I have a new shopping list so that we'll have everything we could possibly need when she comes home and can experiment and see what works best. The following website helped me get some ideas:
My personal favorites are meat tenderizer and flat coca cola for breaking down protein to clean out tubes, and clear nail polish to paint over syringe markings so the lines and numbers don't rub off after constant usage and sterilization. There is a lot more that I have yet to learn, but I have a good start. And despite impending surgery, I'm feeling positive and relaxed about the future.

Thursday, December 6, 2012

And the NICU roller coaster hits a a new low...

So Sunday night I go in for a bottle feed after seeing two separate wheezing/aborted bottle feeds/crying episodes that had caused some of my anxiety in my previous post. I had a message on my phone that earlier in the day her airway had seemed "more reactive" and they were considering putting her back on steriods. When I walk in the room I see she is back on oxygen. And not the low flow kind either.

I lost it. It had been building for a few days, and I could no longer clamp it down. The nurse must have thought I was usually like this. It embarasses me to get so emotional, but I guess I should be proud that I kept it together for over a month of this mess. I almost had to call my work and ask for more time to come back from my lunch break because I couldn't pull it together.

So the next day I am armed with a dozen questions about RAD that all boil down to "what the hell is happening to my daughter!?"  I wait at the hospital 2 1/2 hrs in the morning in vain, because the doctor was too busy to talk to me. I go home to relieve my husband so he can go to work, and I'm unable to sleep. I exhaust my poor mother on the phone pouring out my frustration and fears.

But then the doctor calls me and has exciting news. He thinks she may not have RAD at all and have a "floppy" upper airway that is the cause. It could have gotten irritated by us upping her bottle feeds, so tomorrow he is having an ENT (ear/nose/throat) doctor do a bronchoscopy to examine her upper airway for any problems. He also thinks her reaction to her meds is not as typical as it should be if she really has RAD.

I realize that if she has one of these problems it could me an a G-tube, but at this point I'll take it if it means she can breathe better without all this reactive airway mess. I'm actually excited that something may be wrong with her upper airway, believe it or not. But the ramifications were less scary by far, so I had my fingers crossed for the next morning. I did six hours of research and was armed with the following list of questions, of which I was well educated on each and ready to expand upon if needed:

1. Did the ENT find trachomalacia/laryngeomalacia/pharyngomalacia or subglottic stenosis?

2. Would you classify it as mild, moderate, or severe?

3.  Is it congenital due to her prematurity, or aquired from the pneumonia/RAD? Perhaps a mix of both?

4. What would be the most conservative to the most aggressive treatments, and what are you recommending? (I had extensively researched each of the following treatment options)
  • Growth/time to allow her to grow out of it. That would mean a G-tube.
  • Aortoplexy. If you do an aortoplexy do you also do a concomitant intraoperative bronchoscopy to verify placement?
  • Stents: If I am understanding correctly this is a temporary measure for a few weeks and not a viable solution.
  • Slide tracheoplasty. Probably a more extreme option not necessary for her issue.
  • Supraglottoplasty
So I am ready the next morning. The doctor finally calls, and to my dismay tells me the ENT found nothing. Dr. Treen wants to do a G-tube with a Nissen fundoplication. http://www.pedsurgwmi.com/resources/8704-Nissen-feeding-tube-bro.pdf

My heart sinks, but I had a list of questions for that possibility too, because while I am onboard the G-tube bandwagon I have reservations about the Nissen.
  1. If she is likely to outgrow reflux, isn't a Nissen a permanent solution to a temporary problem? I don't see that a reversal/take down procedure is ever done, and I don't understand how babies can "outgrow" and the Nissen can "relax" physiologically. I didn't really get this one answered directly because she expanded upon the answer and I got overwhelmed.
  2. Aren't fundos done in the first year often redone due to failures? Yes, but does it matter if she really needs it?
  3. Has she seen a GI specialist to confirm the necessity of this and rule out other issues?   What about a PH or impedence probe study, upper GI series, manometry to rule out motility issues? She answered no, that she sees no need to based on what we already know.
  4. Do you do one without the other often? (In the past they were always done together, but new research has them being done less and less in conjuction and dependent on the individual child's issues.) Dr. Treen confirmed she has done her research by telling me she does them together less and less, but is certain that in Tara's case she needs both.
I thought I was prepared, but the doctor's answers made my head swim a bit and I was more than a little upset that my daughter may now need a major surgery. She was so certain that Tara needed it. But her explanation left me a little confused, and it wasn't until hours of thinking and research later I could understand why and how to rephrase my questioning. It seemed that folks who have Nissen's done only sing the praises when their kids had severe reflux with the typical vomiting symptoms that it cured. And they typically get them at 1-2 years old after other medical management has been tried and failed. My daughter doesn't have the typical GERD symptoms, but I suspect and have not had the doctors confirm that her respiratory issues are very GERD related. If so then I am on the Nissen bandwagon. But if not, it seems like maybe too major of a step based on a possibility and not an inevitability. The diagram below trees the expression of GERD, and I can checkoff next to nothing on the left side but at least 6 on the right side in my amateur assessment.

The doctor seemed to be saying that because a G-tube increases the risk of reflux due to the balloon decreasing stomach size and the swallow study showed that thin liquids (i.e. formula in her g-tube diluted by gastric juices then refluxed) cause her to aspirate, then we should do a Nissen  fundo to prevent that from being a concern. But in my mind if she is not currently having silent aspirations and severe reflux issues, it may be a little too prophyalactic.  But then again is the risk of a major aspiration and repeat hospitalizations for aspiration pneumonia to high of a penalty for failure in this decision?

So here is my new list of questions. I am trying to not be "that mother" that asks idiotic questions based off Google and doesn't listen to an experienced and well educated doctor. I just want to make an informed decision and understand it well, and Dr. Treen seems to recognize that when I asked for some time to discuss it further with my husband. She assured me it is a decision she does not take lightly. I'm sure the answers to some of the first questions will answer the latter, but I'm having trouble wrapping my head around it enough to make it less redundant.

Questions for the Doctor:
Bottom Line; If her respiratory symptoms are already significantly affected by GERD then we are on board with the Nissen Fundoplication:

1.    Did swallow study confirm GERD and not just aspirations during feeding or has that diagnosis been confirmed here due to respiratory symptoms? Would you object to an impedence probe test before we go ahead with Nissen?

2.    How controlled do you think her reflux currently is on Prevacid and positioning? Do we think that silent/secondary/reflux aspirations are strongly related to her RAD symptoms or solely aspiration during longer/more frequent feeds we did recently?

3.    Trying to understand why bottle feeds create the exacerbation…..what is the RAD reacting to exactly if ENT says upper airway is normal and no reflux irritation? Can you confirm that the respiratory exacerbation we were seeing the past few days was upper respiratory and not lower? Do you deduce it was reflux related?

4.    It seems like we are doing this prophalactically for what could occur, and not based on confirmation that she has already been having silent/secondary/reflux aspirations. Is that incorrect?

5.    Have we ruled out a motility problem/pyloric stenosis by symptoms? If not don’t we need to do a gastric emptying study, so that we’ll know if a pyloroplasty is in order along with the Nissen?

6.    Why do you think a GJ tube is a bad alternative to the Nissen in her case?

7.    How experienced is the surgeon that will be doing the Nissen/G-tube? Can we meet them? We would like to discuss the AMT Mini-One button option as an alternative to the Mic-Key and whether laparoscopy is possible because of her respiratory status.

8.    How will we know if Nissen was successful? Since she has atypical reflux symptoms, will it just be lack of repeat hospitalizations for aspiration pneumonia? (Most people singing the praises of fundiplication are those with typical vomiting behaviors that are seen to reduce, which she doesn’t really seem to have)

9.    How exactly does a Nissen “relax” and a baby “outgrow” it? What happens physiologically?

10.  With RAD, is it adversely indicated if I even take her for a short walk in the stroller outdoors with no people contact? Should we never leave the house except for Dr. appts?

11.  Why are the doctors and nurses so much less alarmed than I am at how low her oxygen dips during crying fits/wheezing? Do I need to drop everything with my son and spend however long calming her down every time?


Some of the research I did came up with these two tidbits that made me think she already has reflux respiratory issues that are signifcant, and even if that is not the case she could be at high risk from her RAD treatment meds and tachypnea episodes.
·         Many of the modes of pharmacotherapy for a reactive airway, including beta adrenergic agonists and xanthines, can lower LES tone, thereby increasing the propensity for reflux. Also the increased negative intrathoracic pressure from coughing and wheezing and the increased negative intrathoracic pressure from hiccups and stridor can exacerbate reflux.  Winter HS Gastroesophogeal Reflux. Comprehensive Therapy 1989; 15 (2) :  6-10

·         45% of coughing reflux episodes were non-acid reflux. I wonder now how much of her coughing is because of reflux instead of RAD. And non-acid reflux will be missed on a PH probe test but the newer Impedence probe test will capture it.

 I've probably been to 10 times the links I'm including below, but these are some easier to understand articles and anecdotal stories that were helpful:
http://www.jaoa.org/content/100/12_suppl/11S.full.pdf

 I think Google should give me an honorary doctorate.